Proprietary Nanoparticle IP Estates That Enable Nose-to-Brain Peptide Delivery at the Route Level
Nanocarrier IP protects how peptides reach the brain, not just the molecules themselves.
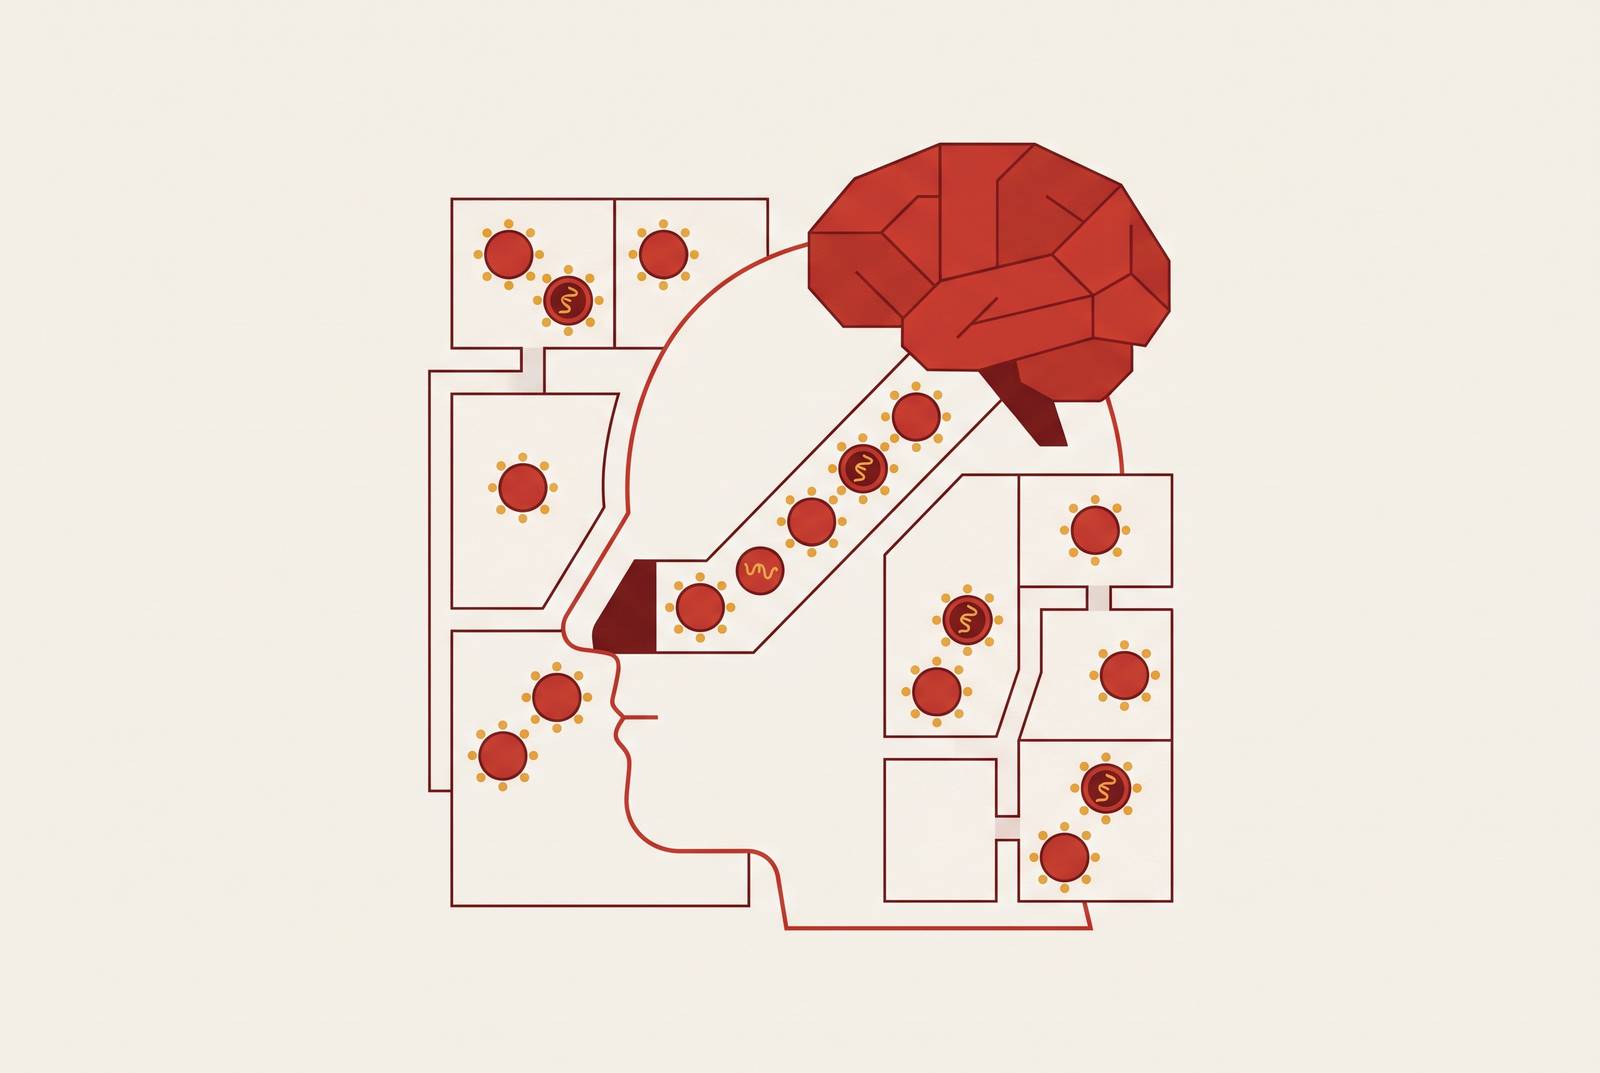
Nanoparticle nose-to-brain delivery for CNS peptide indications depends on solving three problems together, namely mucosal adhesion, enzymatic protection, and epithelial uptake. The nasal route can bypass the blood-brain barrier through olfactory and trigeminal pathways, but that anatomical access does not make bare peptides effective brain-delivery agents. The carrier architecture and the layers of its intellectual property estate give it a lasting edge over competitors that the peptide alone cannot offer.
Why the nasal mucosa defeats bare peptides — and what that means for the route
The nasal mucosa is both an entry point and a barrier. Olfactory and trigeminal pathways lead straight into the central nervous system, so peptides can reach it without crossing the blood-brain barrier from the circulation. Yet peptides deposited in the nose must first survive and traverse the tissue guarding those pathways. Anatomical access is only the starting point. It establishes a possible route, with useful brain exposure still uncertain.
Three barriers act on the peptide at once. Nasal enzymes can degrade it, mucociliary clearance can remove it, and the epithelium limits penetration at useful concentrations. Peptides are enzymatically labile and too hydrophilic to penetrate efficiently on their own. These are not merely different descriptions of poor absorption. They are distinct ways for a dose to fail before it can exploit the direct CNS pathways.
What, then, would improving the peptide alone accomplish? Greater stability would address degradation without necessarily extending nasal residence or improving epithelial uptake. A longer residence would also do little to help if the peptide still could not cross the epithelium. The route therefore imposes a coupled delivery problem that peptide optimization alone cannot resolve. For the route to be useful, the architecture around the cargo must do its part.
What nanocarrier engineering must solve simultaneously to make the route viable
A viable nanocarrier must retain the peptide at the mucosa, shield it from enzymes, and support epithelial transport within the same delivery system. A formulation cannot compensate for failed protection merely by adhering longer, because the extra contact time must preserve peptide capable of uptake. Nor does efficient uptake rescue cargo already degraded.
Chitosan provides a concrete solution to the retention constraint. It is positively charged at mucus pH and binds electrostatically to the negatively charged olfactory and respiratory epithelium. Encapsulation within a nanoparticle matrix addresses a different constraint by protecting the peptide from the nasal enzyme environment and supporting controlled release. Surface charge, ligands, and cell-penetrating peptides, or CPPs, must then support transport across the epithelial barrier.
Conjugating CPPs to nanocarriers can stabilize them in the nasal environment while directing transcellular transport more effectively than co-administration. Arginine enrichment supports transcellular transport, while hydrophobic amino acids support mucus penetration. These modifications give surface chemistry a precise role within the wider architecture, rather than treating it as an interchangeable accessory.
The engineering specification is consequently a balance of dependent functions. An adhesive particle that cannot support uptake stalls at the epithelium. A particle that transports its payload well but fails to protect it carries degraded cargo forward. This interdependence is also the source of replication difficulty, because copying one useful feature does not reproduce the complete route solution.
Why the dominant carrier architectures — polymeric, lipid, and CPP-decorated — each cover different parts of the specification
Polymeric nanoparticles offer a strong starting point for protection and retention. PLGA, chitosan, and alginate belong to this group, with chitosan providing epithelial affinity through its positive charge and PLGA supporting controlled release. Without additional surface functionalization, transcellular transport remains limited relative to actively decorated carriers.
Lipid nanoparticles shift the balance toward membrane interaction. Their biocompatibility and membrane-mimetic properties aid epithelial crossing, while established scalable manufacturing offers a practical advantage beyond transport itself. However, unmodified lipid systems are less mucoadhesive than chitosan-based systems. Contact time can consequently be shorter. Surface modification becomes the bridge between membrane affinity and the residence needed to exploit it.
CPP decoration is a functional layer that targets epithelial transport through conjugation to a carrier surface, leaving the matrix responsible for other constraints. The CPPs themselves also need protection. Oxidation, hydrolysis, and enzymatic degradation can compromise them in the nasal environment if the carrier does not adequately shield them.
Han et al. at King’s College London demonstrated in Small in 2025 that intranasal gold nanorods could deliver a 28-amino acid gut peptide to the brain with minimal systemic exposure. High loading capacity is attractive, but cytotoxicity concerns weaken the clinical case relative to organic architectures. Combining polymeric adhesion, lipid membrane affinity, and CPP-mediated uptake addresses more of the specification than relying on one mechanism alone.
How IP estates are built around route-level mechanisms, not molecule-level novelty
That engineering logic changes the object of patent protection. Claims can address carrier composition, surface functionalization, device-formulation integration, and the transport pathway engaged. The commercial distinction is substantial. A claim that covers a range of compatible payloads can still apply when the peptide being developed changes.
Breadth still depends on the actual claims. A carrier patent does not automatically protect every drug using the nasal route, but a layered estate can restrict several ways of reproducing a delivery solution. Separate protection for retention, shielding, uptake, and device integration can make changing one component insufficient to avoid the protected architecture. This is the structural advantage over protection confined to a peptide sequence.
NeOnc Technologies illustrates the scale of such an estate. Its SEC filings say it has an exclusive USC license that covers 28 issued and 14 pending U.S. patents, plus 65 issued and 28 pending internationally. Its preclinical evidence also suggests that the lead carrier could facilitate nose-to-brain delivery of other pharmaceuticals. MetP Pharma AG illustrates integration across a different set of layers through a comprehensively patented platform spanning formulation, a proprietary unit-dose applicator, and industrial-scale filling technology.
Does peptide patent expiry remove those barriers? Not on its own, because a generic peptide still faces the same mucosal barriers, and any carrier protection that applies covers how it is delivered. Foundational research, continuation filings, and accumulated development experience can deepen that position over time.
What companies are developing intranasal platforms toward brain-directed peptide delivery in 2025–2026
Aptar Pharma announced three new international patent applications on May 28, 2026, focused on enabling inhaled and nasal delivery of peptide-based therapies. Its broader biologics compatibility program assesses interactions between complex biologics, including proteins and nucleic acids, their nanoparticle delivery systems, and nasal and pulmonary hardware. This is an interface position. The focus is on delivery as the formulation and format change, with no claim to ownership of GLP-1 molecules.
Landmark Medicines Ltd. announced on September 29, 2026, that it plans to move its proprietary nasal delivery platform toward a human volunteer study. GLP-1 receptor agonists were selected as the initial application for testing therapeutically relevant peptide exposure through nasal administration. The distinction is consequential. The peptide serves as a test of the platform, although nasal exposure alone would not establish direct brain delivery. The announcement describes a development step toward human validation.
NeOnc reported Phase 2a results for NEO100 describing a notable six-month progression-free survival rate in a mutation-defined subtype of recurrent high-grade glioma. That clinical result is distinct from evidence for peptide delivery. Its relevance here is the combination of an intranasal development program, issued and pending protection across jurisdictions, and preclinical support for additional payloads. Those elements show how many layers the estate has, but do not prove that each new use will succeed.
MetP joins formulation, device, and filling technology within one platform. Independent research institutions have validated its brain-targeting capabilities, and its technology is documented in 67 predominantly peer-reviewed publications. That record gives more reason to trust the technology and adds published prior art. Together, these organizations illustrate convergent investment in delivery systems, though their disclosures are not equivalent demonstrations of nanoparticle-mediated peptide transport into the human brain.
Why GLP-1 peptides are the highest-stakes test case for route-level N2B delivery
A 2025 JAMA Network Open cohort study of U.S. adults found that nearly two-thirds of patients taking GLP-1 drugs for weight management discontinued within one year. Nausea and vomiting are among the most frequently cited reasons for stopping treatment. Treatment loss also begins early. Prescription abandonment before a first fill and discontinuation after that fill make tolerability and delivery central concerns, although discontinuation figures alone do not establish its causes.
The route hypothesis follows from the separation between central action and peripheral exposure. Semaglutide targets appetite-control centres in the brain, while activation of peripheral GI receptors plays a part in nausea and vomiting. Delivering GLP-1 peptides toward hypothalamic appetite centres through the olfactory pathway could preserve the central signal while reducing peripheral GI exposure, a mechanistic proposition still awaiting demonstration of human benefit. A nasal carrier must achieve the required distribution for this mechanism to yield benefit.
The potential CNS scope extends beyond appetite control. A pooled analysis of cardiovascular outcome trials found that people with T2D who used GLP-1RA long term had a much lower hazard of a later dementia diagnosis than those who took placebo. Washington University’s January 2025 study linked GLP-1RA use to lower risks of seizures and addiction to alcohol, cannabis, stimulants, and opioids. Al-Aly at VA St. Louis said the proposed mechanism stems from GLP-1 receptor expression in brain areas that control impulses, reward, and addiction.
Animal evidence of increased synaptic plasticity adds a further mechanistic signal. None of these findings establishes that nasal delivery treats neurological disease. They instead identify hypotheses that depend on reaching relevant neuronal populations. A protected carrier capable of testing those hypotheses would have a development role wider than replacing injections.
The translation gap — where preclinical promise meets clinical uncertainty and what it means for IP strategy
The Alzheimer’s disease findings place a hard limit on that optimism. GLP-1 receptor agonists have not demonstrated clear cognitive benefit in AD, and the 2025 EVOKE and EVOKE+ phase 3 studies did not slow disease progression. Links to lower dementia risk and mechanisms seen in animals do not show that patients who already have the disease will benefit.
Insufficient or poorly targeted brain exposure is one possible explanation. Subcutaneous delivery may fail to achieve the concentrations needed at the neuronal populations implicated in the neuroprotective hypothesis. Yet compatibility with an explanation is not proof. The proposition that nasal nanocarriers would resolve this problem remains mechanistically plausible but unproven in human tissue, and a null result does not identify delivery as the cause.
The route also faces its own translation hurdles. Formulation development, device selection, and nasal biopharmaceutics evaluation complicate movement from preclinical results to human testing. Safety characterization adds another demanding constraint. Manufacturing scalability and regulatory pathways for novel nanocarrier-device combinations must also be addressed before an effective laboratory architecture becomes a usable clinical product.
For IP strategy, uncertainty creates timing value. Organizations building layered protection before human proof may hold a stronger position if their architectures enable peptides to survive and traverse the nasal mucosa. Foundational research, continuation depth, and familiarity with regulatory dossiers accumulate over time. Even an early, extensive patent estate depends on protecting a carrier that ultimately works to support a successful therapy.
Why the carrier architecture, not the peptide, is the platform — and what that means for the scope of N2B IP
Peptides and other biologics delivered nasally require protection, sufficient mucosal contact, and effective epithelial transport. That common specification supports reuse of carrier mechanisms, though it does not establish identical performance for every cargo. NeOnc’s preclinical evidence for delivery of additional pharmaceuticals illustrates the opportunity. The generalizable asset is the architecture, subject to payload-specific validation.
Indication expansion follows the same conditional logic. GLP-1 receptor involvement in appetite, reward, neuroprotection, and synaptic plasticity provides reasons to investigate metabolic disease, addiction, and neurodegeneration. These remain distinct clinical tests. Beyond GLP-1, orexin peptides, neuropeptide Y analogs, and other CNS-active peptides face the same broad mucosal barriers, creating scope for extending an estate where its claims and technical performance support that extension.
Device and manufacturing protection can reinforce this platform breadth. Even when another developer identifies similar carrier chemistry, applicable device or process claims may constrain how that formulation is delivered or produced. As additional payloads and indications are validated, the commercially durable asset the market will ultimately price is the carrier IP estate enabling their delivery.
Sources
- Full article: Can nanoparticle-based intranasal delivery systems revolutionize treatment of central nervous system diseases?
- Nanocarrier-based intranasal drug delivery for enhanced neurological disorders treatment
- Cell-Penetrating Peptide-Decorated Nanovectors for Nose-to-Brain Delivery: A New Treatment Option for CNS Diseases
- Intranasal Nano-Delivery Systems: Emerging Strategies for Central Nervous System Disease Therapeutics - PMC
- Advanced intranasal peptide delivery systems for improved management of Alzheimer's disease - PubMed
- Nose‐to‐Brain Delivery of Acyl‐Ghrelin Peptide Gold Nanoconjugates for Treatment of Neurodegenerative Diseases
- Nose-to-Brain Drug Delivery